INTRODUCTION
KBG syndrome (KBGS) (OMIM#148050) is a multisystem disorder characterized by short stature with growth retardation, distinctive facial features including macrodontia of upper central permanent incisors, and developmental/cognitive delay [1,2]. KBGS arises from variants or deletions, in Ankyrin Repeat Domain 11 (ANKRD11), which is situated on chromosome 16q24.3. ANKRD11 is categorized as one of the ankyrin repeat-containing co-factors [2-4]. Since 1975, when the first KBGS patient was reported, more than 300 cases have been reported [1,3]. Until recent years, KBGS was widely recognized as an exceptionally rare genetic disease. However, with the advancement of genetic diagnostic techniques, there has been a notable escalation in both the diagnosis rate and the number of reported cases, thereby contributing to a rapid increase in its global prevalence. Here, we will review the previously reported and newly reported clinical aspects of KBGS and the related genetic patterns revealed so far are reviewed.
CLINICAL ASPECTS
Although the correlation of genotype-phenotype has not been clarified, it has been suggested that the ANKRD11 variant may be associated with a wider spectrum of clinical features (Table 1).
Table 1.
Clinical features of KBGS
| Major features (≥ 50%) | |
|---|---|
| Intellectual disability and developmental delay | > 90% |
| Macrodontia of upper central incisors | > 60% |
| Distinctive craniofacial findingsa | > 60% |
| Post natal short stature | > 50% |
| Variable skeletal anomaliesb | > 75% |
| EEG abnormalities | = 50% |
| Minor features (< 50%) | |
| Cryptorchidism in males | |
| Hearing loss | |
| Feeding problems, palatal abnormalities | |
| Brain malformations | |
| Behavior problems | |
| Cardiac defect |
aBroad triangular face, short neck, synophrys, hypertelorism, prominent ears or dysplastic helices, bulbous nasal tip, prominent nasal bridge, long and smooth philtrum, and thin upper lip.
bCostovertebral abnormalities, large anterior fontanelle with delayed closure, short and webbed neck, abnormal ribs, brachydactyly, clinodactyly, syndactyly of toes, kyphosis, scoliosis, hip dysplasia or Perthes disease, sternum abnormalities, wormian bones in the skull, clavicular pseudoarthrosis, and osteopenia.
Major features (over 50% in patients)
In more than 90% of individuals with KBG syndrome, there are documented reports of a varying level of intellectual disability (ID) and developmental delay (DD), particularly being prominent features [5,6]. Cognitive skills vary in individuals during childhood, with most experiencing developmental delays, especially in speech. During adulthood, the intelligence of individuals with KBG syndrome spans from moderate impairment to typical levels, with the majority experiencing a mild intellectual disability. While some achieve independence, many require support in daily tasks [1,6-8]. Over 60% of KBGS patients commonly show macrodontia of upper central permanent incisors, distinctive craniofacial findings such as a broad triangular face, short neck, often with synophrys, hypertelorism, prominent ears or dysplastic helices, bulbous nasal tip, prominent nasal bridge, long and smooth philtrum, and thin upper lip [1,6]. Despite presenting with normal growth parameters at birth, over 50% of KBGS patients experience postnatal growth stunting, leading to short stature [1]. Variable skeletal anomalies are common in affected individuals, occurring in 75% of cases. The observed anomalies encompass a wide range of features, such as costovertebral abnormalities, delayed closure of a large anterior fontanelle, a neck that is both short and webbed, abnormal ribs, brachydactyly, clinodactyly, syndactyly of the toes, kyphosis, scoliosis, hip dysplasia or Perthes disease, abnormalities of the sternum, the presence of wormian bones in the skull, clavicular pseudoarthrosis, and osteopenia [1,6,9,10]. Approximately 50% of affected individuals with KBGS exhibit EEG abnormalities, with or without seizures. Seizures may commence anywhere between infancy and adolescence, displaying diverse types of epilepsy. Although tonic-clonic seizures are the most common, there is no exclusive association of a specific epilepsy type with KBGS [1,9].
Minor features (under 50% in patients)
Other known features are cryptorchidism in males, hearing loss, feeding problems, palatal abnormalities, brain malformations, behavior problems such as attention deficit hyperactivity disorder, autism spectrum disorder, anxiety and shyness and cardiac defect [1,6,7].
Possible new clinical features
In a recent case report, the prevalence of strabismus among enrolled 43 participants with KBGS was found to be 23.3%. Additionally, astigmatism, myopia, and hyperopia were reported in 27.9%, 16.3%, and 20.9% of the participants, respectively [11]. In addition, in recent case reports, congenital vaginal agenesis combined with cervical aplasia was reported in a 12-year-old female patient with KBGS, and a patient diagnosed with congenital aganglionic megacolon was also reported [12, 13]. Also, in a few case reports, central precocious puberty in KBGS was reported [7,14,15]. In another recent study, in the constitutive ANKRD11 gene knockout mice, abnormal embryo development and pre-weaning lethality were reported [16]. Ola et al. conducted a study on 42 patients with KBGS, finding higher rates of miscarriage, C-section, premature birth, small gestational age, and NICU admission [16,17].
DIAGNOSTIC METHODS
Genetic diagnostic methods employed for establishing a diagnosis of KBGS encompass targeted sequencing of the ANKRD11 gene, whole exome sequencing (WES), gene panel testing, and whole genome sequencing. In some cases, chromosomal microarray analysis or comparative genomic hybridization can be done to detect microdeletion of 16q24.3. However, based on numerous case reports and related studies, the diagnosis of KBGS was typically not made through a targeted genetic test specifically for the ANKRD11 gene variant. Instead, patients presenting with ID or DD underwent comprehensive genetic testing, such as WES or gene panel testing, when there were clinical manifestations of suspected genetic disorders. In many cases, these tests revealed variant in the ANKRD11 gene, thereby confirming the diagnosis of KBGS. Although there is a lack of universally accepted clinical diagnostic criteria for KBGS, various authors have proposed clinical criteria that can be used for diagnosis. Based on previous studies, if an individual presents with ID or DD along with macrodontia of the upper central incisors or the characteristic facial features mentioned above and postnatal short stature, diagnosing KBGS should be considered [1,3,6].
GENETIC ASPECTS
ANKRD11 gene
ANKRD11 located in 16q24.3, the pathogenic gene responsible for the main phenotype of KBGS, encodes crucial chromatin co-regulator proteins which control histone acetylation and gene expression during neural development (Fig. 1) [3,5]. It functions as chromatin remodelers by engaging with distinct transcriptional repressors or activators situated at both the N- and C-terminals [3,5]. Asli et al. provided evidence showing that ANKRD11 primarily localizes to neuronal nuclei and is involved in modulating neural plasticity [18]. Their investigation revealed that the N-terminal domain is implicated in protein interactions and homodimer synthesis, while the C-terminal domain plays a crucial role in facilitating the degradation of the ANKRD11 protein [3,17]. The exact role of the ANKRD11 in cellular processes and development is not fully understood, but it is believed to play important roles in gene regulation, chromatin remodeling, and protein-protein interactions. In this aspect, Cornelia de Lange syndrome (CdLS; OMIM#122470), Coffin-Siris syndrome (CSS; OMIM#135900), CHOP syndrome (CHOPS; OMIM#616368), and KBGS share certain facial similarities including ID and DD, short stature, and typical facial dysmorphisms due to underlying genetic factors and molecular pathways involved in the developmental process [5,14].
Fig. 1.
ANKRD11 variants at the protein and DNA levels.
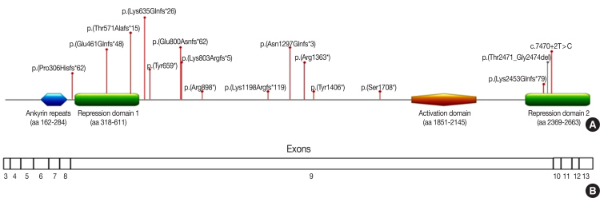
(A) Diagram showing ANKRD11 protein domains and variant positions. Ankyrin repeats (blue), repression domains (green), and activation domain (orange). Loss-of-function mutations (red) and in-frame deletion (gray). (B) Diagram of ANKRD11 exons coding sequence. Exons 6-8 for ankyrin domain, exon 9 for activation and first repression domains, and exons 9-13 for second repression domain. Copy right all reserved at Clinical Genetics, Volume: 100, Issue: 2, Pages: 187-200, First published: 05 May 2021, DOI: (10.1111/cge.13977).
Classification of gene variants
Over 75% of variants in the ANKRD11 causing KBGS are frameshift and nonsense variants [3]. The majority of variants are of de novo origin, with approximately 30% being inherited [19]. Also, deletions of 16q24.3 or parts of ANKRD11 have been frequently reported [5]. In contrast, reports of missense variant have been relatively infrequent [3,5]. In previous studies, variants such as frame shift and nonsense variant tend to be associated with more severe phenotypic presentations of KBGS [1,3-5,7]. Specifically, it is known that a group having a nonsense or a frameshift variant shows more DD, ID or learning difficulties than a group having a missense variant [3]. However, interestingly, in a study conducted on 29 patients with missense variants in the ANKRD11 gene, it was found that the clinical characteristics of patients with missense variants were not significantly different from the typical clinical features observed in patients with nonsense or frameshift variants. They suggested that it was associated with disrupted transrepression capacity and reduced protein stability, and that these missense variants had similar ANKRD11 haploinsufficiency, which has been known as the loss-of-function, as the ANKRD11 gene that causes KBGS [20]. However, the available literature on missense variants is currently limited, with a scarcity of functional and laboratory-based studies conducted on missense variant.
CONCLUSION
This review focused on the clinical and genetic characteristics of rare KBGS. Since the phenotype of KBGS is variable and non-specific even though in same family, clinical diagnosis of KBGS is not easy and could be missed [5]. Moreover, it might be difficult to suspect KBGS based only on the clinical features or clinical findings and proceed with the target gene test since some syndromes share clinical features including ID and DD, short stature, and typical facial dysmorphisms [5,13]. However, early diagnosis and timely management of KBGS could be crucial to improve its prognosis. Thus, genetic analysis for ANKRD11 gene could be considered the patient who has short stature with ID and DD and further study about its variable clinical multi organ manifestations is needed to identify and diagnose more KBGS patients. In addition, subsequent molecular investigations and studies regarding chromatin co-regulation and the expression of the ANKRD11 gene in various organs are needed.